Habijabi Logo

হাবিজাবি-৩৮৯

respiratory
**********************************************************************
Author:Dr Kawsar Uddin (DMC K-65)
2 min read
August 4, 2026 at 12:18 PM
25 comments
2 images
Media File (1/2)
Episode illustration

#হাবিজাবি_৩৮৯

৫৪ বছরের পুরুষ রোগী। normotensive, nondiabetic. কয়েকদিন ধরে তার বুকে ব্যথা। মাঝে মাঝে শ্বাসকষ্টও হয়। তার নিজের একটা ব্যাখ্যা আছে,

"ডাক্তার সাহেব, অনেক বছর আগে রাজমিস্ত্রীর কাজ করতে গিয়ে বুকের ডান পাশে ইট পড়েছিল। মনে হয় সেই ব্যথাটাই আবার উঠেছে। মাঝেমাঝে ওঠে, ব্যথার ওষুধ খেলে ভালো হয়ে যায়, এবার আর হচ্ছেনা।"

অনেকে রোগীর নিজস্ব diagnosis explanation কে সত্যি ধরে নিয়ে চিকিৎসা শুরু করেন, সেখান থেকেই শুরু হয় anchoring bias. রোগীর ছেলে তাকে নিয়ে গেল নিকটস্থ কুয়েত মৈত্রি হাসপাতালে। তারা

হার্টের সমস্যা সন্দেহ করে পাঠিয়ে দিলো National Institute of Cardiovascular Diseases (NICVD)-এ! chest টা একটু auscultate করলেই রোগের কারণ খুঁজে পেত।

NICVD তে যেয়ে Troponin-I, Electrolytes, Creatinine করলো, সব স্বাভাবিক, রায় হলো - হার্টের সমস্যা নয়। সম্ভবত Musculoskeletal pain হিসেবে ডিসচার্জ দেয়া হলো।

দুই দিন ধরে দুইটি বড় হাসপাতালে ঘুরলেন। কিন্তু ছোট একটা কাজ ভালোভাবে করা হয়নি, কেউ chest auscultation করেনি, করলেই clean cut findings of consolidation.

আমার কাছে এসে রোগীর জিজ্ঞাসা

প্রশ্ন একটাই, "ডাক্তার সাহেব, এটা কি গ্যাস্ট্রিকের ব্যথা?" এই অবস্থায় কেউ হয়তো endoscopy ও করে ফেলতো!

হিস্ট্রিতে শুরুতে Musculoskeletal pain মনে হলেও, respiratory system examination এ chest expansion reduced in right side, right chest base এ bronchial breath sound, vocal resonance বেশি, percussion dull note.

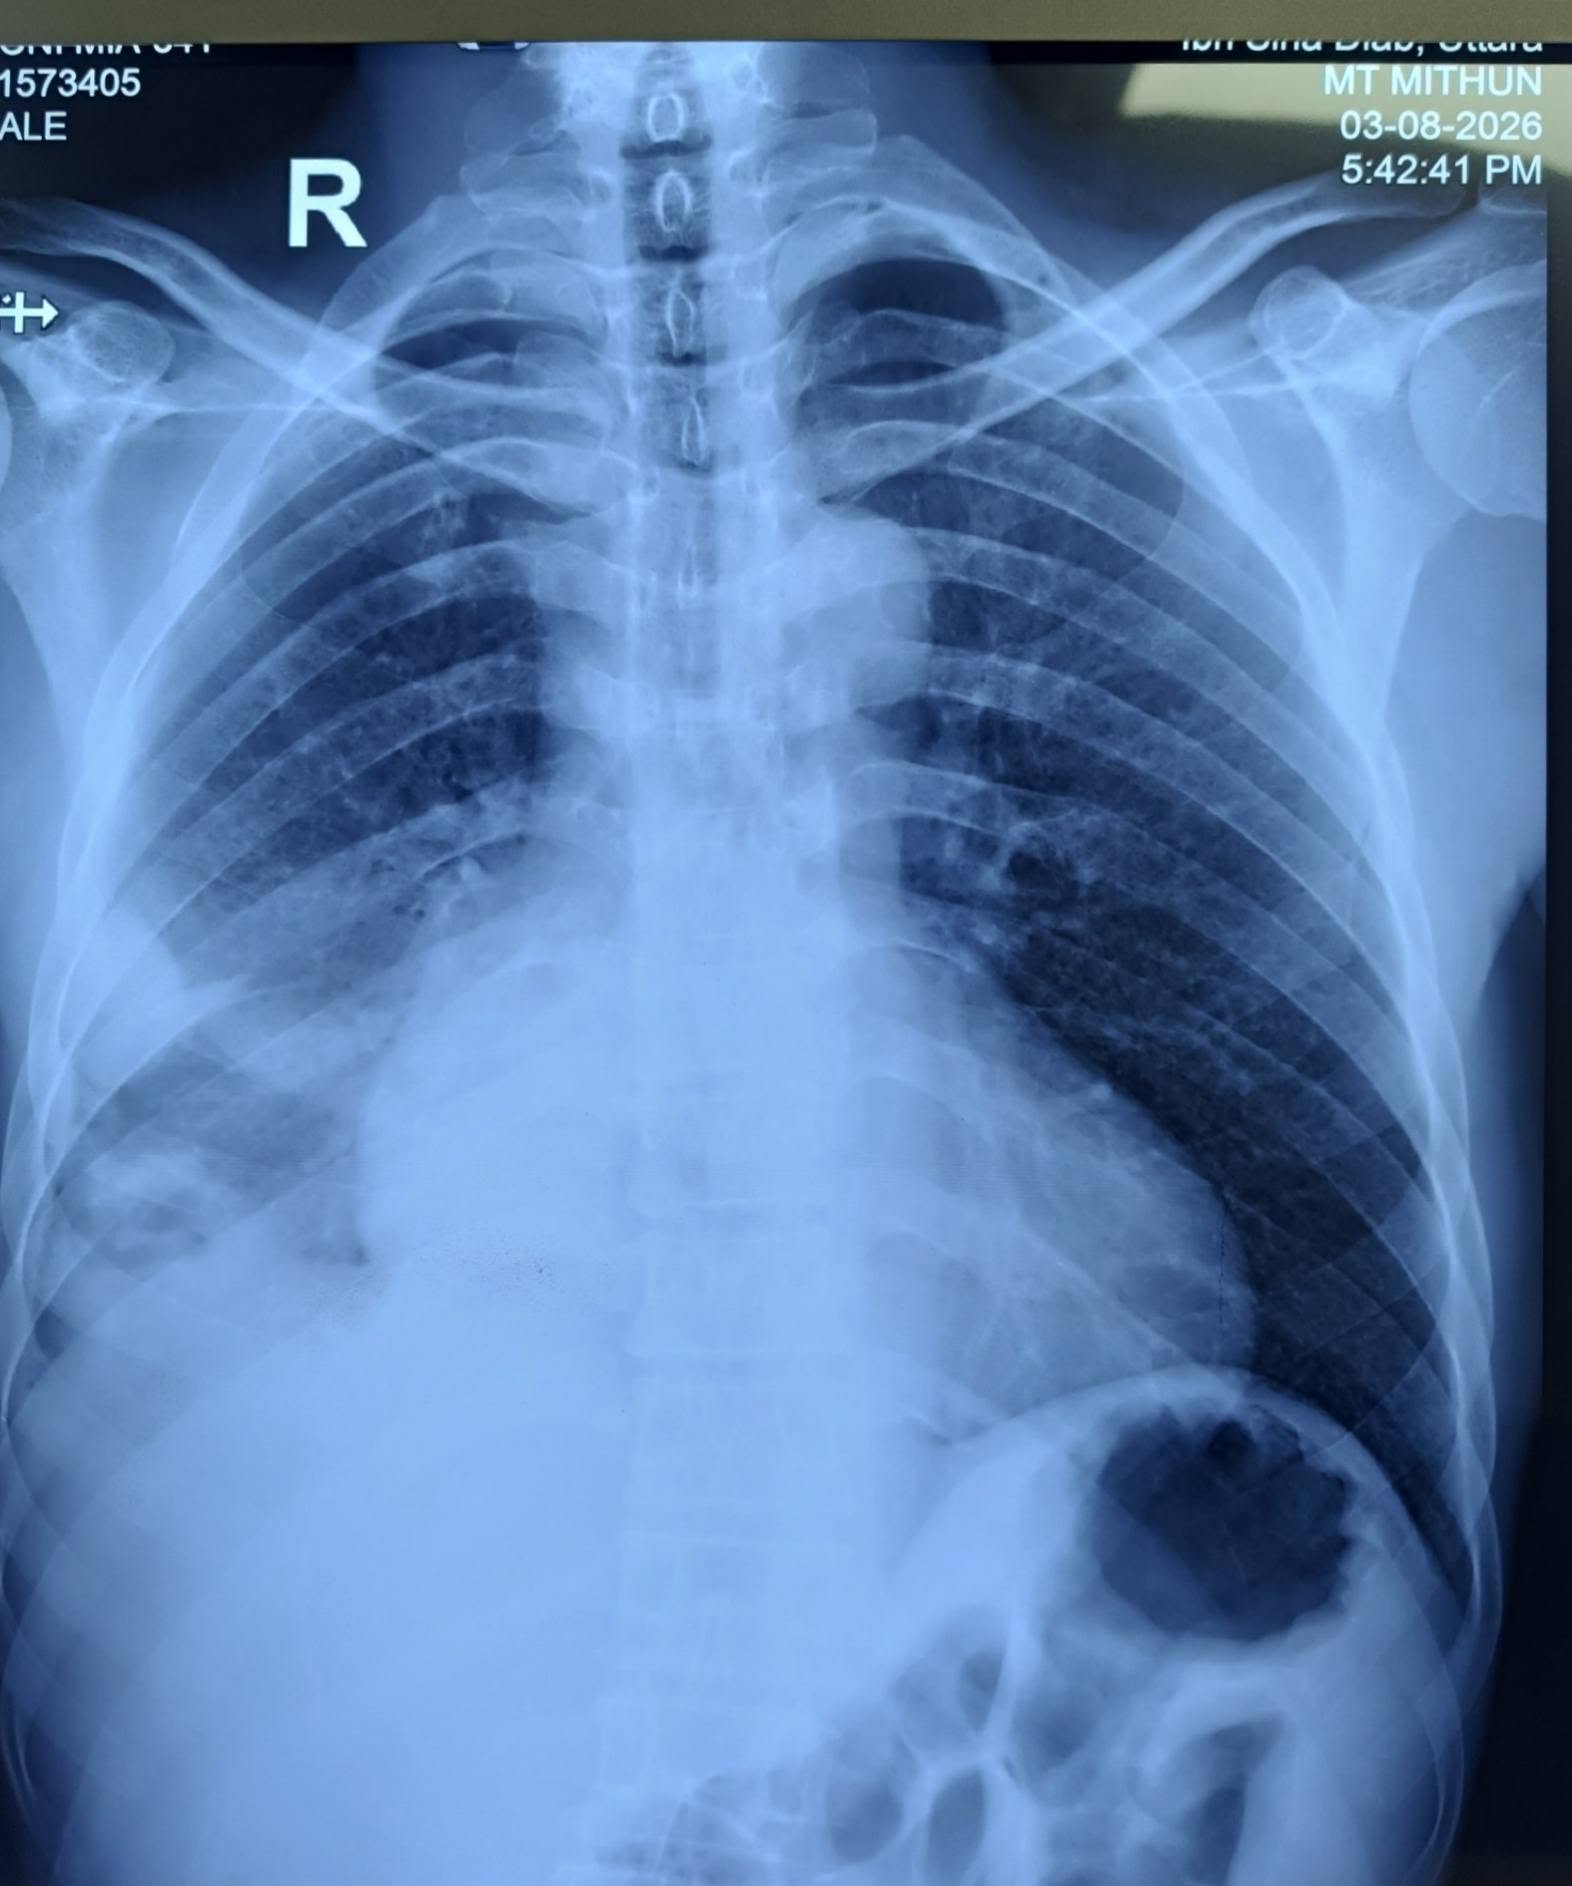
এক কথায় Consolidation. Chest X-ray দিলাম। ১০ মিনিট পর x-ray film হাতে আসতেই সব পরিষ্কার। ডান ফুসফুসের middle ও lower lobe এ consolidation with air bronchogram অর্থাৎ Pneumonia. রোগীর বুকের ব্যথার কারণও এটাই!

আধুনিক চিকিৎসাবিজ্ঞানে Investigation এর গুরুত্ব অপরিসীম। কিন্তু Investigation কখনো Clinical Examination এর বিকল্প নয়। সঠিক জায়গায় stethoscope না ধরে চিকিৎসা শুরু করলে, অনেক সময় রোগ আমাদের সামনে থেকেও ধরা পড়ে না।

Sir William Osler এর বাণী,

"Listen to your patient, he is telling you the diagnosis."

এর সাথে আরেকটা লাইন যোগ করি,

"And examine your patient carefully; the body often confirms what the history is trying to tell you."

কাওসার

কে-৬৫

keywords:PneumoniaConsolidationAir bronchogramAnchoring biasChest painClinical examination

Comments (25)

Steve_minecraft111
1d

এট লিস্ট রিব ফ্র্যাকচার এক্সক্লুড করার জন্যও তো এক্সরে দেয়ার কথা ছিল প্রথমেই

Kawsar Uddin
1d

Steve_minecraft111 exactly

Anonymous_panda2726
1d

Seems like a cavitary lesion in lower zone. Plz also consider that.

Kawsar Uddin
1d

Anonymous_panda2726 considered. Necrotizing pneumonia হয়ে হতে পারে। abscess এর বাকি ফিচার এখনো নাই, আশা করি সেদিকে আর progress ও করবে না, antibiotics started.

Ahmad Hoque
1d

Kawsar Uddin dm pt der klebsiella jehetu common Cavitary lesion niye ashe. As you said necrotizing pneumonia

Kawsar Uddin
1d

Ahmad Hoque pt is non diabetic.

Rakib Al Imran
1d

Rt side e D shaped lesion & Cavitary lesion with possible air fluid level. Empyema+ Lung abscess? But Fever, Cough to obossoi thaka ucit.

Kawsar Uddin
1d

Rakib Al Imran D shaped lesion is an old traumatic hematoma. calcified subsequently. obvious air fluid level is not obvious, but as it is pneumonia, which can necrotize & form abscess, could be early abscess as symptoms are not suggestive yet.

Khairul Shimon
1d

Yes cough might be missed during story writing

Kawsar Uddin
1d

Khairul Shimon Sir, patient has a history of chronic cough (mild), could be due to chronic dust exposure as he is a construction worker, smokers cough as well. No recent exacerbation of cough, even cough was not a complaint at all, rather chest pain which increases on movement, cough reflex & breathing. No sputum production.

Khairul Shimon
1d

Kawsar Uddin so it might be atypical infection ..

Md Ataur Rahaman
1d

এই রোগীকে এত এত পরীক্ষা দেয়া হলো অথচ গরীবের CBC টা ই দেয়া হলো না। আর যা ই করুক না কেনো- এটা থেকে তো ধারণা পাওয়া যেতো। পরে যা করার করতো।

Kawsar Uddin
1d

Md Ataur Rahaman exactly

Md Saiful Islam Sajem
1d

Thanks for sharing Vai. Sometimes just simple x-ray and CBC along with history and just simple clinical examinations ( which was supposed to be done by the attending physician) is enough to reach the diagnosis. You are an inspiration Vai. I always try to do physical examinations whenever I see any patients and most of the time I try to write the important clinical examinations findings and my clinical dx in my prescription. Thanks vai

Kawsar Uddin
1d

Md Saiful Islam Sajem Thanks for your kind words & insightful opinion. A careful history, thorough physical examination, and a few basic investigations often point us in the right direction. I really appreciate your prescription practice, many physicians don’t write symptoms & examination findings nowadays, even no diagnosis at all probable or differential. Wishing you all the best

Md Saiful Islam Sajem
1d

Kawsar Uddin boro Vai

Shahid Alam
1d

Massive pleural effusion er pt ke patailam medicine e admit howar jonne.. Pt ghure msk pain diagnosis hoye amr kache ashlo ekdin por.. Keu amr lekha prescription dekhlo na.. Pt kache x ray cilo oita dekhlo na.. Ei hosse obostha

Kawsar Uddin
1d

Shahid Alam pathetic scenario in many centres

Tansib Jaman
1d

· Reply

Comment attachment
MemorableTiger9376
1d

এখন প্রায় সবাই নন টাচ টেকনিকে রোগী দেখে। রোগীর গায়ে হাত দেয়ার সময় কারোও হয় না। এটা কে ফিড ব্যাক হিসেবে নিবেন।

Kawsar Uddin
1d

MemorableTiger9376 very true

Israt Jahan
1d

Nousheen Tabassum Ahona

Unknown
1d

What about fever sir?In pneumonia there should be fever as far as a I know.

Kawsar Uddin
1d

Anonymous member 811 Fever was not his complaint. But on query he was feeling feverish.

Kawsar Uddin
22h

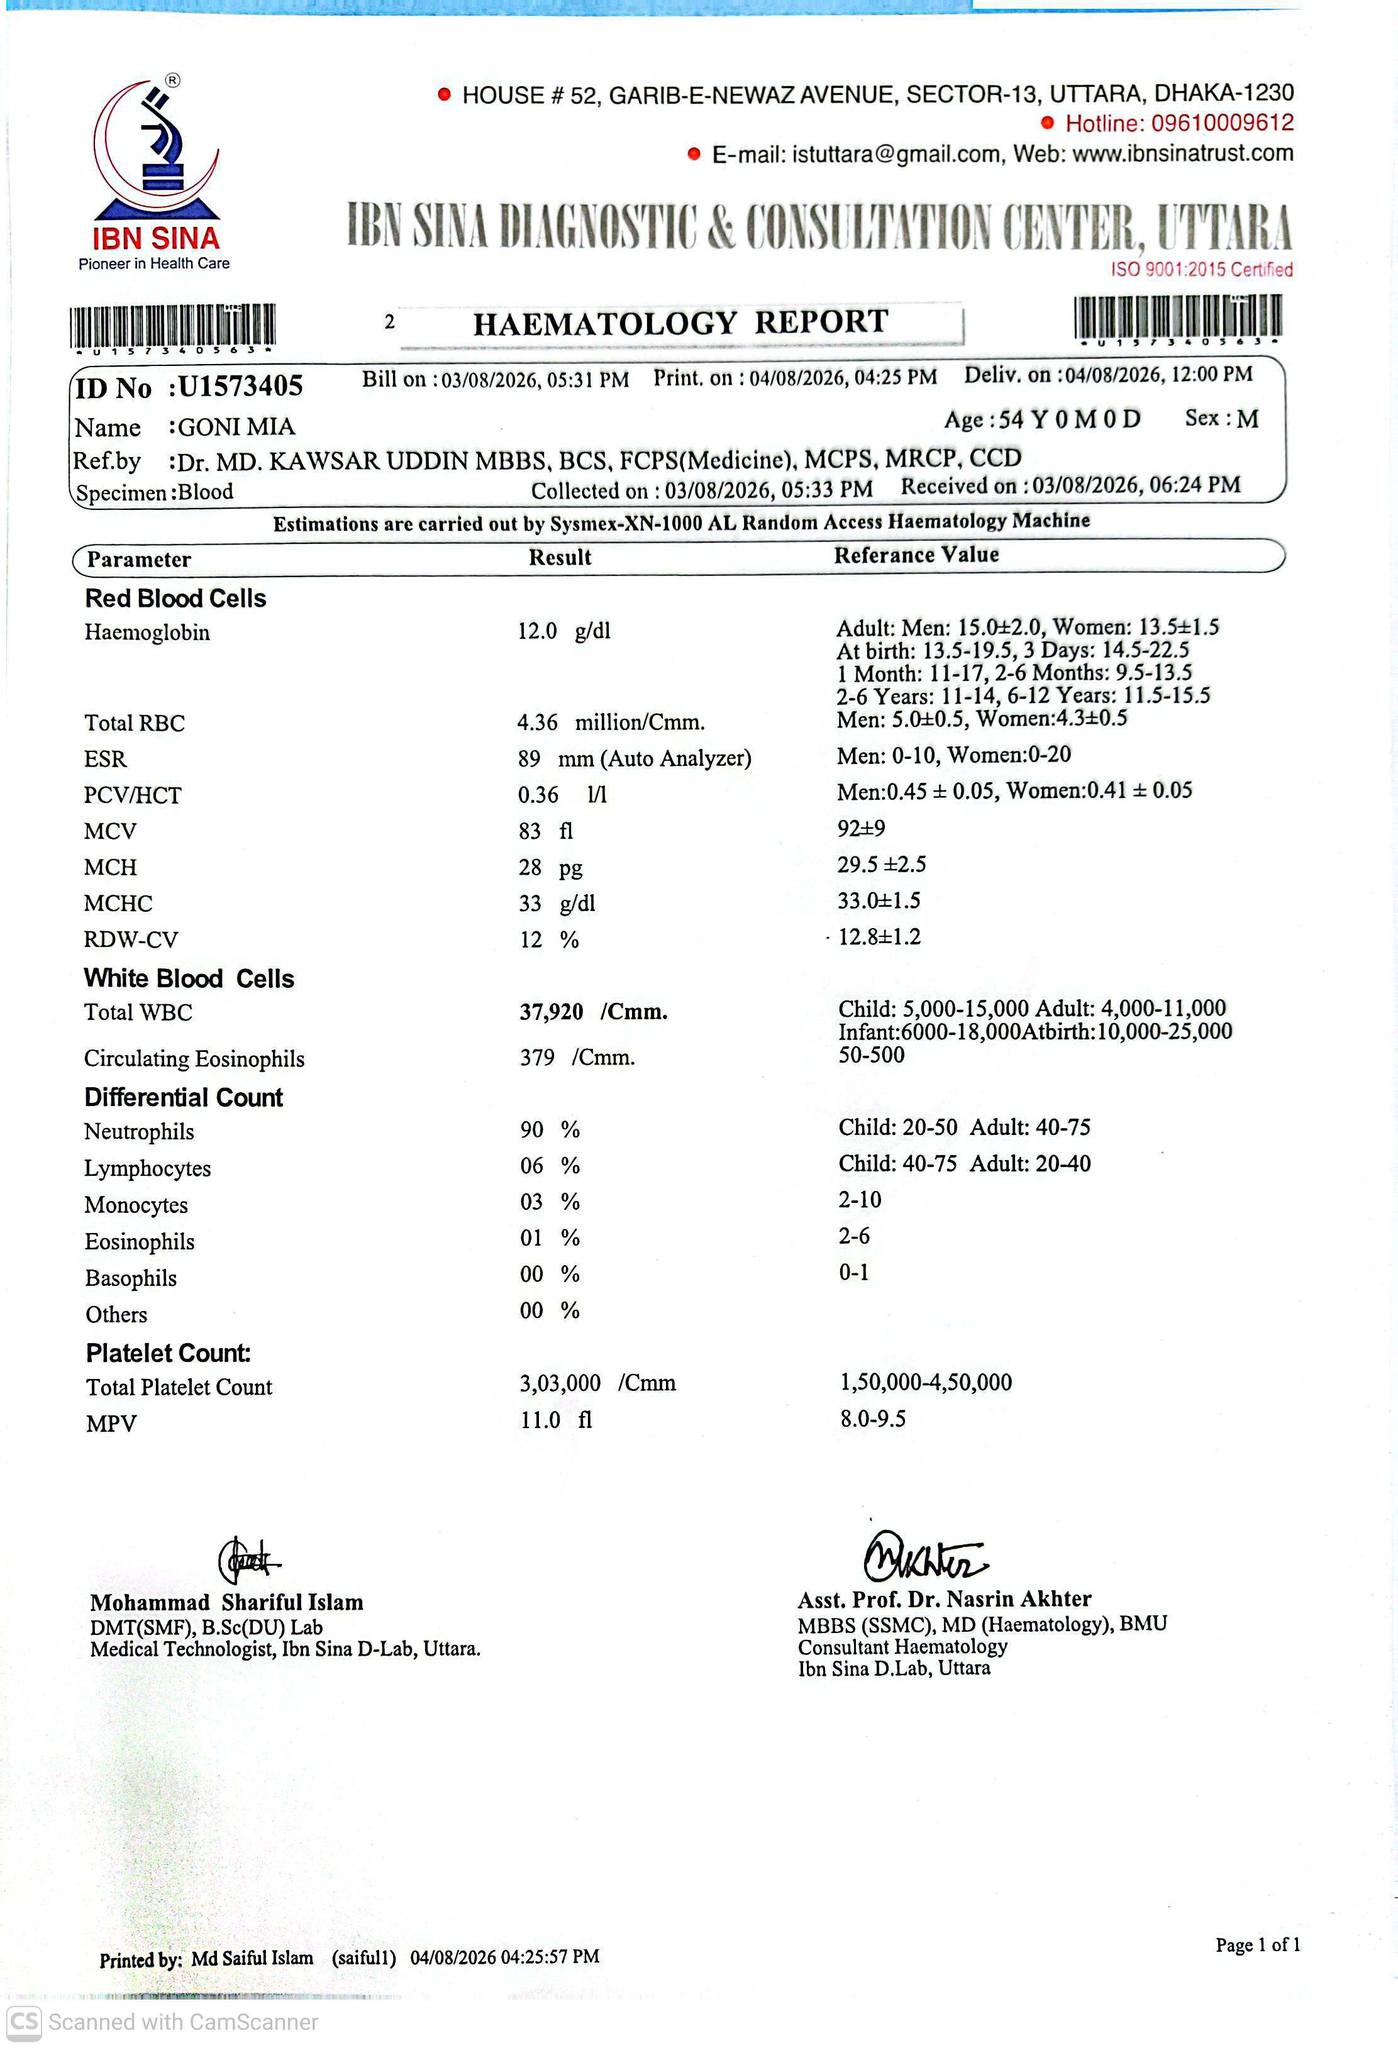
Patient's CBC. WBC is very high. Antibiotics along with NSAID were already prescribed the day before of test report & patient is feeling better just in a day.

Comment attachment